[email protected]
+1 (502) 904-2126
One Westbrook Corporate Center, Suite 300, Westchester, IL 60154, USA
Site Map
 ISSN: 2574 -1241
Received: September 22, 2026; Published: October 05, 2026
*Corresponding author: Li Ye, Naxi District People’s Hospital, Luzhou City, Sichuan Province, China
DOI: 10.26717/BJSTR.2026.67.010426
Objective: This study compares the medium-to long-term clinical outcomes of novel elastic micromotion implants
versus conventional subcutaneous tibiofibular screws in the treatment of acute combined inferior tibiofibular
injuries, analyzing ankle joint functional recovery, radiographic reduction quality, and complication rates
between the two groups, thereby providing evidence-based references for the selection of clinical internal fixation
strategies.
Methods: This retrospective cohort study enrolled 76 patients with acute distal tibiofibular joint injury admitted
to our hospital between February 2020 and May 2022. The patients were divided into an observation group
(38 cases receiving fixation with the novel elastic micro-motion implant) and a control group (38 cases receiving
rigid fixation with traditional cortical screws). Perioperative clinical parameters were collected from both
groups, and a medium-to-long-term follow-up was conducted for 1,836 months postoperatively. The following
outcomes were recorded: AOFAS ankle and foot function score, VAS pain score, ankle range of motion, loss of
distal tibiofibular reduction, and complications related to internal fixation. The functional outcomes at the final
follow-up visit and the incidence of adverse events were compared between the two groups.
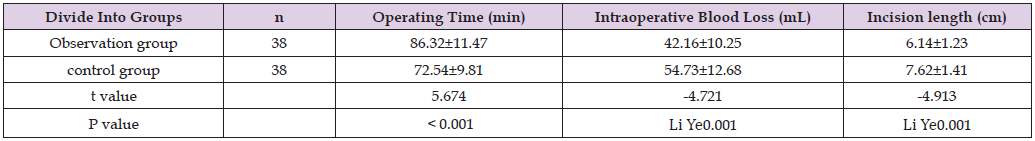
Results: The observation group exhibited a longer operative duration compared to the control group (P<0.05),
while the intraoperative blood loss and surgical incision length were superior to those in the control group
(P<0.05). All patients completed follow-up visits, with a median follow-up period of 26.2 months. At the last
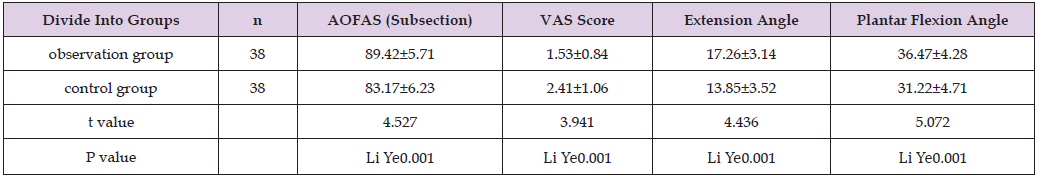
follow-up, the AOFAS score in the observation group (89.42±5.71) was higher than that in the control group
(83.17±6.23), and the VAS pain score (1.53±0.84) was lower than that in the control group (2.41±1.06); additionally,
the ankle dorsiflexion and plantar flexion range of motion in the observation group was superior to
that in the control group (P<0.05). The overall complication rate was 10.53% in the observation group versus
28.95% in the control group, with a statistically significant difference (P<0.05); however, the proportion of secondary
surgeries due to screw fracture or screw removal was higher in the control group. Imaging findings
indicated that the incidence of reduction loss was lower in the observation group compared to the control group,
although this intergroup difference was not statistically significant (P>0.05).
Conclusion: For acute distal tibiofibular syndesmosis injuries, long-term follow-up with the novel elastic micro-
motion implant has been shown to yield superior ankle joint function and lower rates of internal fixation-related
complications, while preserving the physiological micro-movement of the tibiofibular syndesis and avoiding
the need for secondary pin removal surgery—making it suitable for patients with high demands for ankle
joint mobility; however, this approach involves a longer surgical learning curve and requires strict attention to
the quality of intraoperative reduction.
Keywords: Distal Tibiofibular Syndesmosis Injury; Elastic Micromotion Implant; Screw Fixation; Ankle Joint; Medium-to Long-Term Follow-Up; Complications of Internal Fixation
General Information
A retrospective analysis was conducted on 76 patients with acute distal tibiofibular syndesmotic injuries admitted to the Department of Orthopedics at our hospital between February 2020 and May 2022.
• Inclusion Criteria:
(1) Acute distal tibiofibular syndesmotic injury confirmed by imaging studies, with a time interval between injury and surgery <14 days;
(2) Unilateral injury;
(3) Age range of 18–65 years;
(4) Complete surgical records and pre-and postoperative imaging data;
(5) Follow-up duration ≥18 months.
• Exclusion Criteria: Open ankle joint injuries; history of prior ankle trauma or surgery; concurrent severe neurovascular injuries; severe osteoporosis; and cases with lost-to-follow-up status. This study was approved by the Hospital Ethics Committee; patient informed consent was waived, and the study adhered to the Declaration of Helsinki for Medical Research Ethics. A total of 76 patients were enrolled into the observation group (receiving the novel elastic micro-motion implant, n=38) and the control group (receiving traditional cortical screw fixation, n=38). The observation group consisted of 22 males and 16 females, with a mean age of 40.7 ± 9.6 years; the control group comprised 24 males and 14 females, with a mean age of 41.3 ± 10.1 years. There were no statistically significant differences between the two groups in terms of age, gender, injury type, or the time interval between injury and surgery (P> 0.05); thus, the baseline characteristics were comparable.
Surgical Procedure
All surgeries were performed by the same team of foot and ankle surgeons; all procedures utilized combined spinal-epidural anesthesia, and patients were positioned in the supine position.
Control Group (Conventional Cortical Screws): Following ankle reduction, Kirschner wire was used for temporary fixation; C-arm fluoroscopy confirmed proper reduction of the distal tibiofibular fracture. Two 3.5 mm cortical screws were implanted, penetrating three layers of tibial and fibular cortical bone to achieve rigid fixation; concurrent plate-screw fixation was performed for any associated fractures of the medial or lateral malleolus. Postoperative shortterm cast immobilization was applied; at 8–12 weeks postoperatively, the patient was referred back to the hospital for a secondary surgery to remove the distal tibiofibular screws, followed by a gradual weight-bearing rehabilitation program.
Observation Group (New Elastic Micro-Motion Implant): Complete fracture reduction and temporary Kirschner wire fixation, then confirm anatomical reduction of the distal tibiofibular syndesmosis via fluoroscopy; according to the product operating guidelines, create a bone tunnel and implant a novel elastic micromotion implant. The implant’s elastic structure permits physiological micro-displacement between the tibia and fibula while maintaining sufficient fixation strength; after adjusting the tension, lock the implant in place, eliminating the need for secondary implant removal surgery. For patients with concomitant ankle fractures, perform fracture reduction and internal fixation in a single procedure. Initiate passive ankle joint mobilization in the early postoperative phase, then progressively transition to partial weight-bearing and full weight-bearing based on soft tissue healing progress, without requiring a secondary screw removal surgery.
Both groups received routine postoperative anti-infective therapy, edema reduction and pain management, early ankle joint rehabilitation guidance, and regular outpatient follow-up X-ray examinations.
Observation Indicators
1) Perioperative indicators: operative duration, intraoperative blood loss, surgical incision length
2) Follow-up functional parameters: AOFAS ankle-hindfoot score at the last follow-up, VAS resting pain score, ankle dorsiflexion and plantarflexion range of motion.
3) Imaging findings: Repeat radiographic examination to assess loss of reduction of the distal tibiofibular syndesmosis and signs of traumatic arthritis.
4) Complications: surgical site infection, internal fixation breakage, internal fixation irritation, loss of reduction, number of reoperations; calculate the overall complication rate.
Statistical Treatment
Statistical analyses were performed using SPSS 26.0 software. Measurement data are expressed as , and inter-group comparisons were conducted using the independent samples t-test; enumeration data are expressed as number of cases and percentage, and the χ² test was employed, with Fisher’s exact test applied when the expected cell counts were insufficient; the significance level was set at α=0.05, and a P-value <0.05 was considered statistically significant.
Comparison of Perioperative Indicators
(Table 1).
Table 1: Comparison of perioperative parameters between the two patient groups 
Medium-to Long-Term Follow-Up Functional Outcome Measures
All 76 patients were fully followed up for a total follow-up period of 1,836 months, with a median follow-up duration of 26.2 months. At the final follow-up, the observation group demonstrated superior AOFAS scores and ankle range of motion compared to the control group, as well as lower VAS pain scores; these inte
Table 2: Functional outcomes at the final follow-up for the two groups
Complications
The observation group experienced a total of 4 complications (10.53%), including 1 case of superficial incisional infection and 3 cases of local implant-related irritation; no cases of implant fracture or secondary surgery were reported. The control group experienced a total of 11 complications (28.95%), including 3 cases of screw fracture, 2 cases of incisional infection, 2 cases of loss of reduction, and 4 cases of pain or local irritation associated with screw removal; a total of 7 cases in the control group required secondary surgery. The overall complication incidence rate between the two groups was compared (χ² = 4.070, P = 0.044), indicating a statistically significant difference. Regarding imaging-confirmed loss of reduction, there were 2 cases in the observation group and 6 cases in the control group; the intergroup comparison yielded P = 0.261, indicating no statistically significant difference.
The tibiofibular joint is a micro-mobility joint; during ankle movement, there is a normal, minimal displacement of the distal tibia and fibula. Rigid screw fixation eliminates this physiological micro-movement, which represents a significant biomechanical factor contributing to postoperative screw fracture and ankle stiffness. During medium- to long-term follow-up, although traditional screw fixation can achieve early stabilization, it necessitates a secondary surgical procedure to remove the screws, thereby increasing both the patient’s surgical trauma and the overall medical burden; however, some patients decline screw removal due to fear of undergoing a secondary surgery, which significantly elevates the risk of screw fatigue fracture following prolonged weight-bearing activity. The long-term follow-up results of this study indicate that the group receiving the novel elastic micro-motion implant achieved superior outcomes compared to the traditional screw group in terms of AOFAS scores, ankle range of motion, and pain scores, while also demonstrating a lower overall complication rate. This implant preserves the physiological micro-motion of the tibiofibular joint, allowing for moderate intertibiofibular displacement under weight-bearing conditions—thereby better aligning with the biomechanical characteristics of the ankle joint—and eliminates the need for secondary removal, thereby avoiding the traumatic risks associated with screw removal surgery [1].
However, the observation group experienced longer operative times, as the novel implant imposes higher requirements for bone tunnel alignment and reduction quality; consequently, surgeons must adapt to this new procedural approach, which entails a certain learning curve. These findings are consistent with the conclusions drawn from previous studies on elastic fixation devices [2]. In this study, there was no statistically significant difference in the incidence of loss of reduction between the two groups, indicating that elastic micromotion implants do not increase the risk of loss of reduction. However, strict anatomical reduction must be achieved during the operation, as inadequate reduction can directly lead to functional decline in the medium to long term. Regardless of the type of internal fixation used, confirming anatomical reduction of the tibia and fibula under intraoperative fluoroscopy remains a critical procedural requirement [3]. In the observation group, a small number of cases exhibited local irritation at the implant site, which was attributed to contact between the implant and soft tissues or inappropriate placement of the bone tunnel; such adverse reactions could be mitigated by optimizing tunnel placement and ensuring proper management of soft tissues [4-8].
Compared to conventional rigid fixation with cortical screws of the distal tibia and fibula, the novel elastic micromotion implant for the treatment of acute distal tibiofibular joint injuries demonstrates superior ankle joint function, lower rates of internal fixation-related complications, and avoidance of secondary screw removal procedures during long-term follow-up over 1,836 months. This approach also better aligns with the biomechanical characteristics of micromotion in the distal tibiofibular joint. However, this technique entails a prolonged learning curve, demands precise intraoperative anatomical reduction and accurate bone tunnel placement, and requires thorough patient evaluation as well as standardized surgical techniques in clinical practice.
Supported by Luzhou Science and Technology Program (No. 2024SYF189).

International Association of Landscape Archaeology, Czech Glass Society, Czech Republic

Department of Chemistry, Semenov Institute of Chemical Physics, USSR Academy of Sciences, Moscow, Russia

Associate Professor at Department of Breast and Thyorid Surgey, Chongqing General Hospital, China

Professor of Nuclear Medicine, Faculty of Medicine and Surgery, University of Milan, Milan, Italy

Department of Pharmaceutical Sciences, South University School of Pharmacy, USA





 Abstract
 PDF




























